


Welcome to Amanda's NICU Education



RNC-NIC Exam Prep & NICU Education for Nurses
I'm Amanda, a neonatal Clinical Nurse Specialist, NICU educator, and NICU nurse who's been caring for critically ill newborns since 2009.
I currently work as a Clinical Nurse Specialist in a Level IV NICU in Los Angeles, where I support neonatal nurses, providers, and families through education, evidence-based practice, and clinical expertise.
I created Amanda's NICU Ed to make high-quality NICU education more approachable and to help nurses feel more confident at the bedside and prepared for the RNC-NIC exam.
NICU Education for Nurses at Every Stage
Whether you're preparing for the RNC-NIC, starting your career in the NICU, or looking to strengthen your neonatal nursing knowledge, Amanda's NICU Ed provides practical, evidence-based education designed specifically for NICU nurses.

RNC-NIC Exam Prep
Prepare for the RNC-NIC with focused review materials, study resources, and practical test-taking strategies.

NICU Education
Build your knowledge and confidence with approachable education covering the concepts NICU nurses use every day.

NICU Resources
Find study guides, books, free resources, and educational content to support your growth as a neonatal nurse.

Not very many people love taking tests but as a self-acclaimed "forever student" who has taken (and passed) five different certification exams I am no longer afraid of tests! "Way to brag", you might be thinking but I want to help YOU pass your certification exam too!
Introducing Amanda's RNC-NIC Success digital course - your ultimate study companion!
Gain unlimited, on-demand access for life, ensuring you're primed to ace your certification exam.
I'm here to help you succeed and I can't wait for you to share with me that you PASSED the RNC-NIC EXAM!!!

Elevated Lactate in Newborns: What NICU Nurses Need to Know
The Lactate Is 6. Now What?
Understanding Lactate at the Bedside
"What's the lactate?"
You hear it when a baby is critically ill, after a rough delivery, or when a baby suddenly isn't looking quite right.
But what are we actually trying to learn from that number?
At the most basic level, lactate gives us a clue about what's happening at the cellular level. When tissues aren't getting enough oxygen, cells lean harder on anaerobic metabolism and lactate rises.
That's the version most of us learned, and it leaves a lot out. Lactate can be high in a baby with plenty of oxygen on board. A baby can be acidotic with a completely normal lactate. And a high lactate can belong to a baby who is already getting better.
To understand why, we have to go all the way down to the cell (like Ms. Frizzle! Anyone else watch The Magic School Bus as a kid?) and then bring that information back to the bedside.
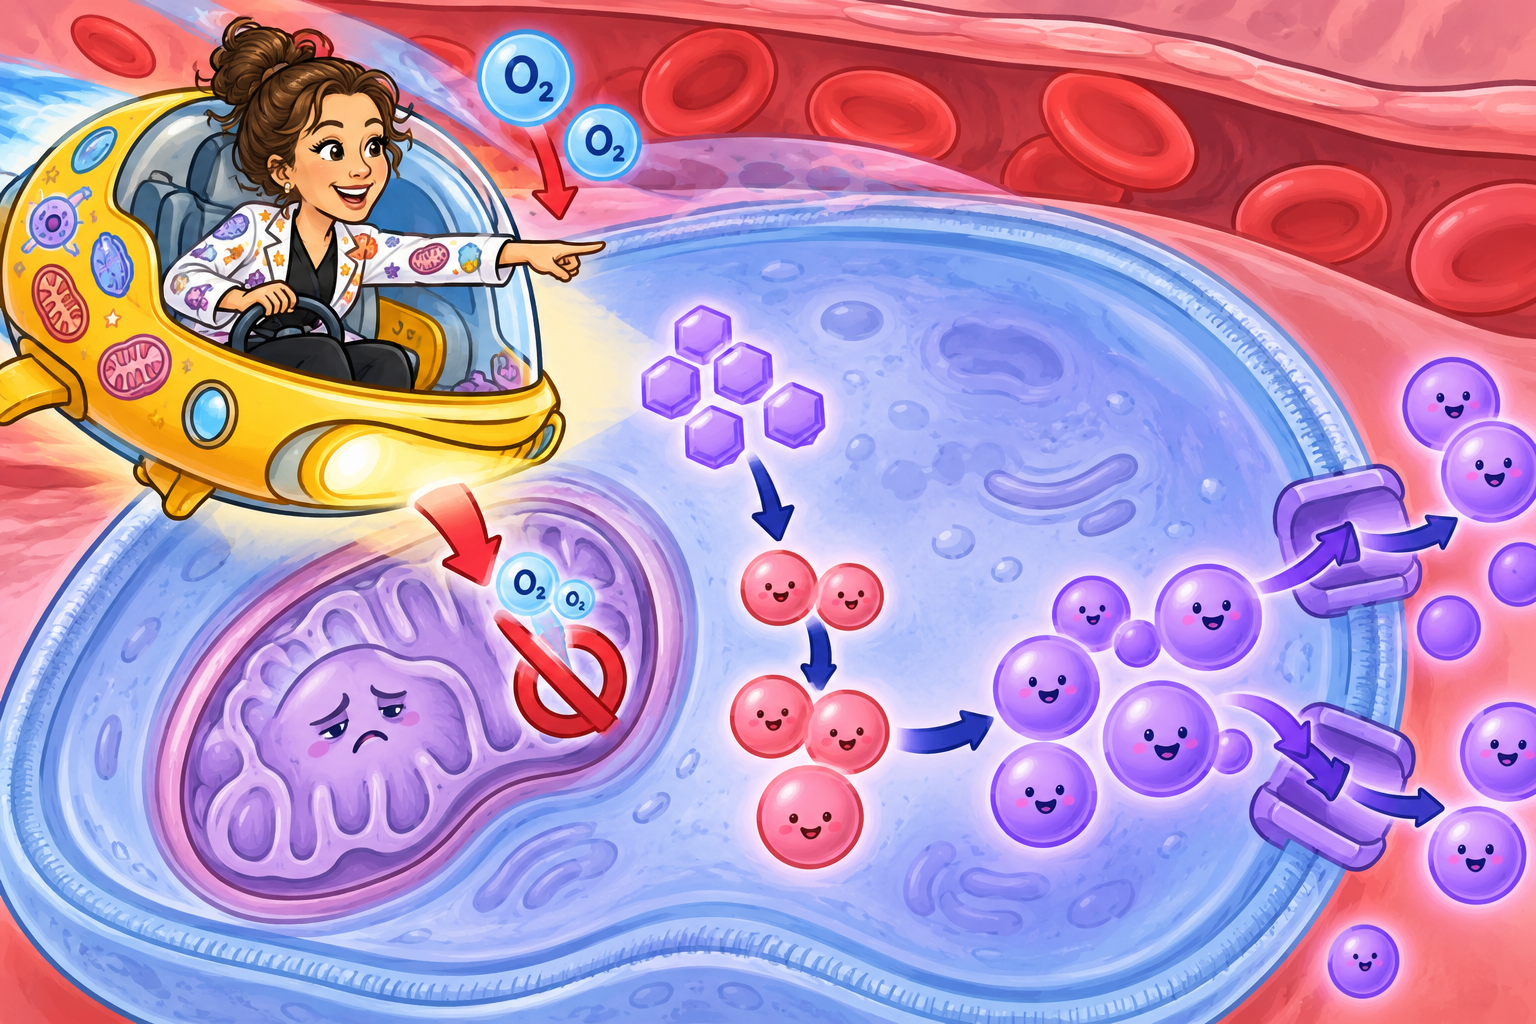
The quick answer: What does lactate tell me?
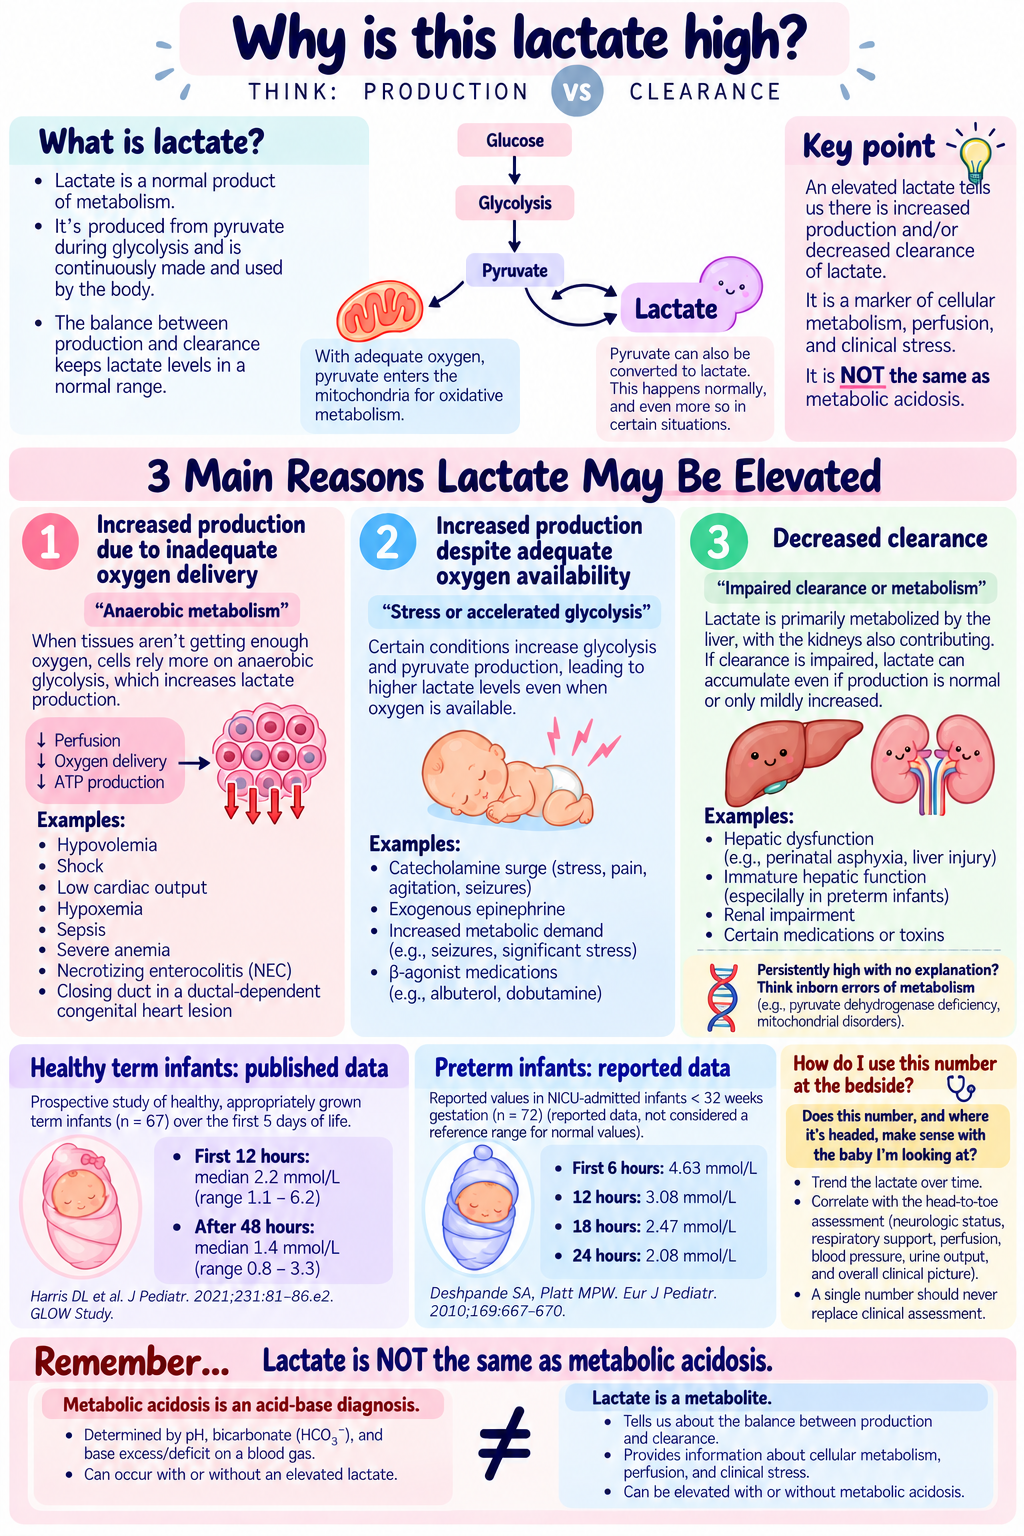
Lactate is a normal product of metabolism. When it's elevated, think about the balance between two things:
Production ↔ Clearance
A high lactate means production is up, clearance is down, or both.
In a sick newborn, inadequate oxygen delivery and poor perfusion are big reasons production goes up. They aren't the only reasons, which is why you can't read a lactate by itself.
Wait...why isn't lactate normally zero?
Because your cells make lactate even when everything is working the way it should.
During glycolysis, glucose becomes pyruvate. Pyruvate can head into the mitochondria for oxidative metabolism, or it can be converted into lactate. Both happen during normal metabolism.
So having lactate in the blood doesn't mean something is wrong. The question is whether it's being produced and cleared at a rate that keeps the level appropriate for this baby's age and clinical condition.
Why does lactate go up?
There are three broad reasons I want us to think about when we see an elevated lactate.
1. Oxygen delivery isn't keeping up
This is the classic mechanism. Picture a baby in shock. Oxygen delivery to the tissues falls, the cells still need ATP, and oxidative metabolism can't keep up. Metabolism shifts toward anaerobic glycolysis and lactate production climbs.
↓ perfusion → ↓ oxygen delivery → altered cellular metabolism → ↑ lactate
At the bedside, that looks like:
Sepsis
NEC
Hypovolemia or blood loss
Low cardiac output (including a closing duct in a baby with a ductal-dependent heart lesion)
Severe anemia
Significant hypoxemia
The baby who just came through a difficult resuscitation
Here the lactate is asking you a question: are oxygen delivery and perfusion adequate to meet what the tissues need?
2. Production is up even though oxygen is available
This one surprised me.
During significant physiologic stress, catecholamines speed up glycolysis. Think about what that epinephrine is telling the body…
We need energy. NOW.
Glycolysis accelerates and makes a lot of pyruvate. Some of that pyruvate gets converted to lactate even though oxygen is still available. You can see this with endogenous catecholamine surges, seizures, and other states of high metabolic demand.
You can also see it with the epinephrine we give. A baby gets started on an epi drip, and the next gas shows a higher lactate and a higher glucose. That can be the epinephrine doing exactly what epinephrine does. It doesn't prove the baby is worse. It doesn't prove the baby is fine either, so you go back to your assessment.
Elevated lactate ≠ proof of tissue hypoxia.
3. Clearance is down
The body has to do something with the lactate it makes. The liver does most of that work, and the kidneys help.
If clearance is impaired, lactate can pile up even when production isn't dramatically increased. Think about the baby whose liver took a hit during an asphyxial event, or the baby in shock whose liver and kidneys aren't being perfused well.
And if a lactate stays high in a baby who looks well perfused, and nothing in the story explains it, bring it up with the team. Liver dysfunction and inborn errors of metabolism live in that category.
Of course, a critically ill newborn can have more than one of these going on at the same time.
Lactate is not the same thing as metabolic acidosis
Metabolic acidosis is an acid-base diagnosis. Lactate is a metabolite.
A baby can have metabolic acidosis with a normal lactate. An extremely preterm infant can develop metabolic acidosis because immature kidneys don't handle bicarbonate and acid well yet. That baby can be well perfused, with a normal lactate, and still be acidotic.
It works the other way too. A baby can have an elevated lactate without significant metabolic acidosis.
So if I'm asking, "Does this baby have metabolic acidosis?" I'm looking at the blood gas: the pH, bicarbonate, and base excess or base deficit, in context.
If I'm asking, "Is this baby making too much lactate, or not clearing it?" I'm looking at the lactate. And then I'm asking why.
So what is a "normal" lactate in a newborn?
We covered that it isn't zero.
Like some of our other labs, lactate changes after birth. Healthy term newborns can run higher during the immediate transition, then come down over the following hours and days.
There isn't one neonatal lactate value that applies to every infant. Interpretation depends on:
Gestational age
Postnatal age
Arterial, venous, or capillary sampling
Collection and processing
Laboratory methodology
What was happening to the baby when the sample was drawn
One prospective study followed 67 healthy, appropriately grown term infants using capillary samples. Median plasma lactate was about 2.2 mmol/L in the first 12 hours of life (range 1.1 to 6.2), falling to about 1.4 mmol/L after 48 hours (range 0.8 to 3.3) (Harris et al., 2021).
Look at that first range again. Healthy term babies, up to 6.2!
I'd be cautious about memorizing one number and calling everything above it abnormal. Know your institution's neonatal reference ranges, then put the number into clinical context.
What about premature infants?
This matters even more in premature infants. We don't have one universally accepted "normal lactate" for an extremely premature infant across the first hours and days of life.
In one study of 72 NICU-admitted infants born at less than 32 weeks (Nadeem et al., 2010), mean lactate concentrations were:
Age | Mean lactate (mmol/L) |
0 to 6 hours | 4.63 |
12 hours | 3.08 |
18 hours | 2.47 |
24 hours | 2.08 |
Lactate came down substantially over the first 24 hours.
Don't read these as a normal reference range. They're observed values from a NICU population that included some very sick babies. The spread was wide (a standard deviation of 3.69 mmol/L in the first 6 hours), and values above 5.6 mmol/L were associated with adverse outcomes.
What they do show: gestational age AND postnatal age both matter when you interpret a lactate.
The premature infant is going through an enormous physiologic transition. Add respiratory distress, resuscitation, hemodynamic transition, temperature instability, catecholamine release, medications, and immature organ function, and one lactate value gets a lot harder to interpret.
Is lactate actually reliable in premature infants?
I got this question on an Instagram post, and it made me think… It depends on what we mean by reliable.
Are we asking, "Did the analyzer accurately measure the lactate in this blood sample?"
Or are we asking, "Does this lactate perfectly represent this baby's tissue perfusion and oxygen delivery?"
The answer to the first is mostly yes. The answer to the second is no, and it was never going to be.
The measurement itself holds up
Studies comparing arterial and capillary lactate drawn at the same time in neonates, including premature infants, have generally shown good agreement.
One neonatal study comparing 193 paired capillary and arterial samples found a very strong correlation between the two (Fauchère, et al., (2002). Another found a mean difference of only 0.17 mmol/L between capillary and arterial values (Frey & Losa, 2001).
But lactate changes on its own
That same study took four capillary lactates within 24 hours in 30 stable premature infants. The values varied by about 20% from one measurement to the next (Frey & Losa, 2001). These were stable babies with nothing going on.
So imagine seeing:
2.0 → 2.3 mmol/L
Technically, the number went up. It's also within the range lactate moves by itself.
This is why I don't want you overreacting to a small change in one lab value. Ask whether there's a meaningful trend, and whether that trend matches what you're seeing in the baby.
Can I trust a heel-stick lactate?
Generally, yes. Capillary lactate gives clinically useful information in neonates.
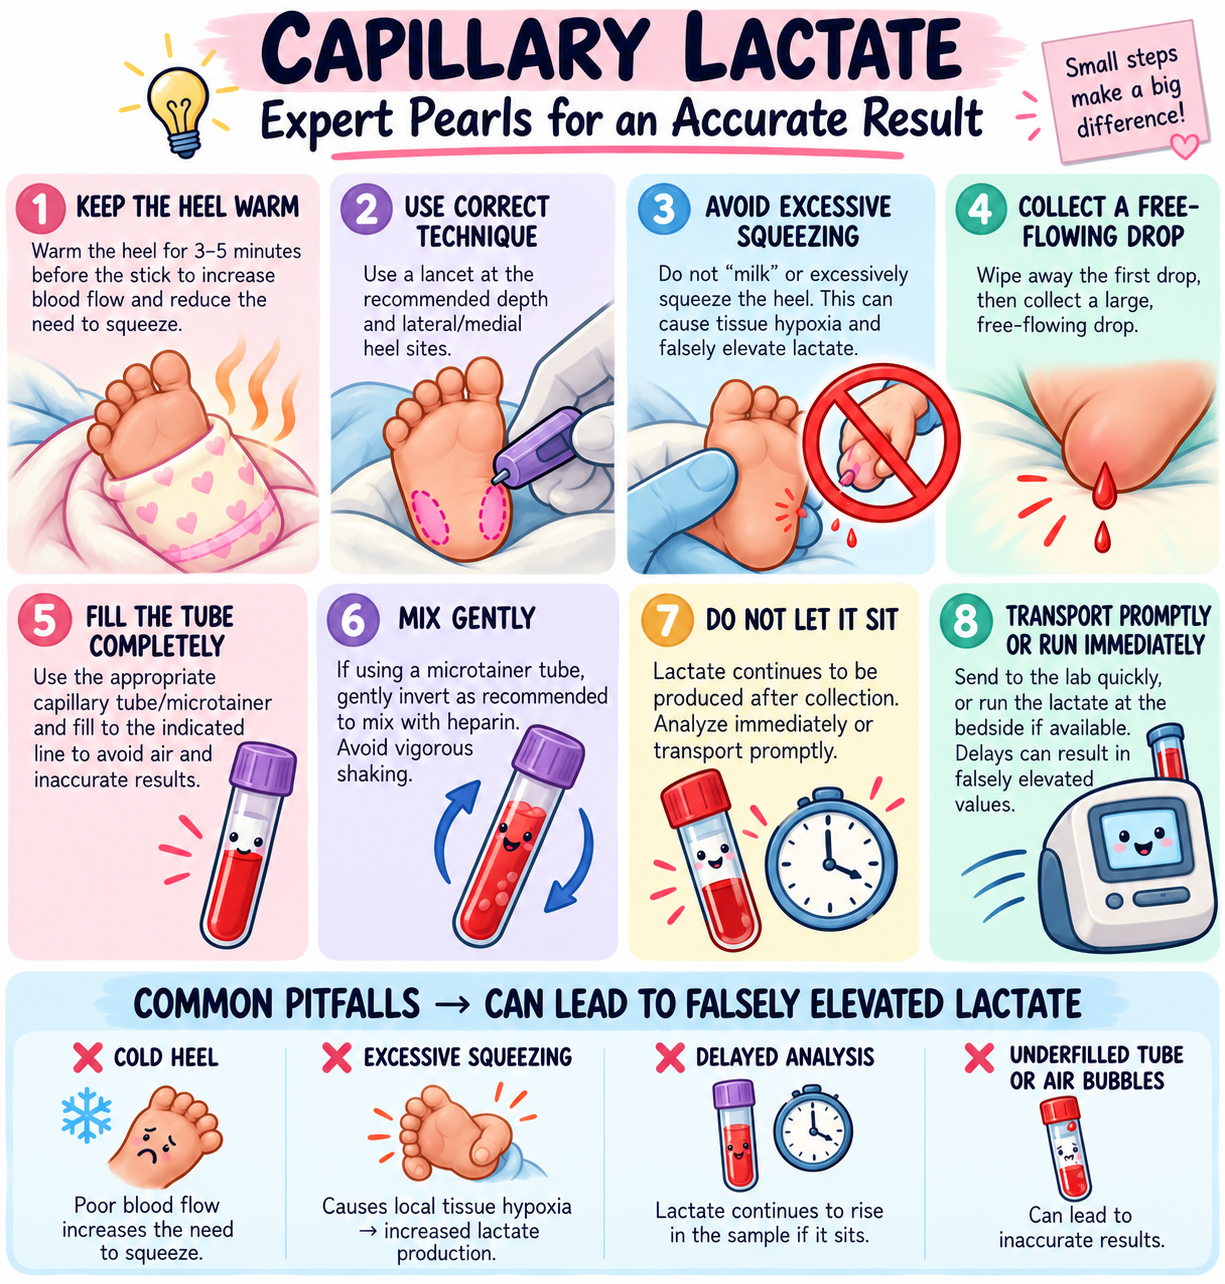
Collection conditions still matter. A sample from a warm, well-perfused heel is not the same as a hard-won sample from a cold, vasoconstricted, hypotensive baby.
And know what can result in erroneous values:
A sample that sits before it's run keeps making lactate in the tube, so a delayed sample can read high.
A lot of squeezing to get the sample can push the number up too.
So if a lactate seems wildly out of step with the baby in front of you, don't immediately assume your assessment is wrong. Think about where the sample came from and how it was collected. Look at the rest of the gas. Look at the values before it. And if it still doesn't fit, talk to the baby's physician, NNP, or PA about repeating it.
The lactate is 6. Now what?
Back to the bedside.
You attend the delivery of a term infant who needs significant resuscitation. At first the baby has poor tone, poor respiratory effort, and evidence of impaired perfusion. Then things start to turn around.
Thirty minutes later:
Heart rate is 145
Blood pressure is appropriate
FiO₂ is down from 100% to 30%
Capillary refill is 2 to 3 seconds
The baby is breathing spontaneously
Tone is improving and the baby is moving on their own
Then the blood gas comes back. Lactate: 6.2 mmol/L.
Is the baby getting worse?
Probably not. That lactate is one piece of information from one moment in time. It likely reflects the metabolic stress and impaired oxygen delivery that happened during the resuscitation. Lactate made during the event can stay elevated after the baby has started to improve, and it comes down over hours, not minutes.
That doesn't mean we ignore it. Here's what I would do with it.
Look at the baby. Is this baby better, the same, or worse than 30 minutes ago?
Question the sample. Where was it drawn, how hard was it to get, and how long did it sit?
Read the rest of the gas. pH, bicarbonate, base deficit, glucose.
Find out when the next one is due. One number can't show you a direction. If nothing is ordered, ask.
Talk to the team if the baby and the number don't match, or if both are heading the wrong way.
The lactate is a snapshot
A lab value gives you one point in time. You see what happened before that sample, while it was being drawn, and for the hours afterward. That is information the lab doesn't have.
So don't let the lactate replace your assessment. Put it next to your assessment.
Neuro: Alertness, tone, spontaneous movement, respiratory drive. Any abnormal movements or concern for seizures? Remember that seizures can raise lactate all by themselves.
Respiratory: Is the FiO₂ going down or creeping up? Are goal sats getting easier or harder to hold?
Perfusion: Heart rate, blood pressure trend, pulses, cap refill, warmth, color.
Urine output: Lots of things affect it, but next to everything else it's another clue about perfusion and organ function.
The rest of the labs: pH, bicarbonate, base deficit, glucose, and where each one is headed.
Same lactate. Two very different babies.
Both babies start with a lactate of 6 mmol/L.
Baby A: 6 → 4 → 2
Perfusion is improving, FiO₂ is coming down, blood pressure is appropriate, and the neuro exam is reassuring. This baby is recovering.
Baby B: 6 → 8 → 10
Cap refill is getting longer. The baby is hypotensive, needs more oxygen, is making less urine, and the acidosis is getting worse. Maybe the neuro exam is changing.
Same starting number. Completely different trajectory.
A 2023 meta-analysis of more than 46,000 neonates found that higher lactate levels were associated with greater morbidity and mortality. But a single lactate, used by itself, wasn't a great predictor. It missed some babies who went on to have poor outcomes and flagged many more who did fine. The authors' recommendation was to focus on serial measurements instead of one value (Matsushita et al., 2023).
What about a baby with HIE?
After significant perinatal hypoxia-ischemia, a high lactate fits the history. It supports that the baby went through substantial metabolic stress and impaired oxygen delivery.
But lactate alone doesn't diagnose HIE, grade the encephalopathy, or decide whether a baby qualifies for therapeutic hypothermia. Cooling criteria are generally built on the perinatal history, the pH and base deficit, and the neurologic exam. Follow your institution's criteria.
For a baby who is being cooled, lactate is still useful as part of the overall trajectory.
Do you trend lactates in your HIE patients?
When should I be worried?
There isn't one lactate number that replaces clinical judgment or your unit's escalation criteria.
Get concerned when an elevated or rising lactate shows up alongside a baby who isn't improving or is getting worse:
Worsening perfusion or prolonged capillary refill
Hypotension or a blood pressure trend you don't like
Increasing respiratory support or FiO₂
Worsening metabolic acidosis
Decreasing urine output
A changing neurologic exam or seizure activity
Temperature instability
A belly that's changing
Or simply a baby who looks different from your last assessment
Any of those should send you back to the bedside to reassess, and then to the baby's physician, NNP, or PA according to your unit's escalation process.
A lot of the time, your assessment will worry you before the labs do.
In summary
Lactate is a metabolite that tells you about the balance between production and clearance. When it's elevated, ask:
Is oxygen delivery inadequate?
Is production up even though oxygen is available?
Is clearance impaired?
Then ask the one that matters most at 2am:
Does this number, and where it's headed, make sense with the baby I'm looking at?
Where to go from here?
If you want more on perfusion, shock, and the drips we use to treat it, that's my Shock & Vasoactive Drugs for NICU Nurses.
If you're studying for your RNC-NIC or CCRN-N, this kind of "why behind the number" thinking is what my review course is built on. Check it out here
Let me know you came from here, use the promo code BLOG and get 10% off!
References
Frey, B., & Losa, M. (2001). The value of capillary whole blood lactate for blood transfusion requirements in anaemia of prematurity. Intensive Care Medicine, 27(1), 222–227.
Harris, D. L., Weston, P. J., & Harding, J. E. (2021). Alternative cerebral fuels in the first five days in healthy term infants: The Glucose in Well Babies (GLOW) Study. The Journal of Pediatrics, 231, 81–86.e2. https://doi.org/10.1016/j.jpeds.2020.12.063
Nadeem, M., Clarke, A., & Dempsey, E. M. (2010). Day 1 serum lactate values in preterm infants less than 32 weeks gestation. European Journal of Pediatrics, 169(6), 667–670. https://doi.org/10.1007/s00431-009-1085-y
Fauchère, J. C., Bauschatz, A. S., Arlettaz, R., Zimmermann-Bär, U., & Bucher, H. U. (2002). Agreement between capillary and arterial lactate in the newborn. Acta paediatrica (Oslo, Norway : 1992), 91(1), 78–81. https://doi.org/10.1080/080352502753458003
Matsushita, F., Krebs, V. J., & De Carvalho, W. D. (2023). Association between Serum Lactate and Morbidity and Mortality in Neonates: A Systematic Review and Meta-Analysis. Children, 10. https://doi.org/10.3390/children10111796


NEONATAL CERTIFICATION
REVIEW BOOK
📌 What’s Inside:
- 13 comprehensive chapters covering core NICU certification content
- Clear, organized breakdowns for fast recall
- Peer-reviewed to ensure clinical accuracy and depth
- Ideal for RNC-NIC or CCRN-N prep — or as a reference guide for NICU nurses at any level
- Plenty of space to write in and take notes
📚Table of Contents:
- Maternal Health & Birth History
- Intrauterine to Extrauterine Transition
- Neonatal Resuscitation
- Thermoregulation
- Neurologic System
- Respiratory System
- Oxygen, Ventilation, & Acid-Base Balance
- Cardiovascular System
- Nutrition & Feeding
- Hematopoietic System
- Infection & Immunology
- Professional Practice


Ready to kickstart your journey to becoming a certified NICU nurse?
Look no further!
Grab my FREE E-Book packed with essential study and test-taking strategies for the RNC-NIC.
In the E-Book I give you the resources you need including the link to access the candidate guide, several types of books to study from, some of my favorite strategies, an outline of the content you should review, and a blank calendar for you to make your study plan!
Frequently Asked Questions About the RNC-NIC exam

What is the RNC-NIC?
The RNC-NIC is a competency-based exam that tests the specialty knowledge of nurses in the United States & Canada who care for critically ill newborns and their families.
The RNC-NICU is a nationally recognized certification that recognizes the registered nurse for their specialty knowledge and skill.

Who can take the RNC-NIC exam?
Nurses can take this exam after a minimum of two years experience in the NICU caring for critically ill newborns and their families.

Which books should I use?
I'm glad you asked! There are many excellent books to help you prepare for the RNC-NIC, I gathered ande describe each of them for you in my FREE e-book.
Is there a course to help me study?
Yes! Many hospitals host their own certification course and there are a few online courses. See my RNC-NIC test taking tips E Book for more information
What happens if I don't pass the exam?
If you don't pass the exam on your first try you can try again after 90 days. You will have to reapply after 90 days and pay a retest fee. There is no limit to the number of times you can take the exam (however a candidate can only sit for the exam twice per year).
Can I make more money if I take the RNC-NIC exam and get certified?
Yes! Many hospitals provide a raise or a bonus for nurses with specialty certifications. Hospitals also typically hire at a higher base salary when nurses have a certification.


Find me @amandasnicued on these channels or Email me
hey nurses don't miss out
© Copyright 2024. AmandasNICUEd. All rights reserved. | Terms & Conditions | Privacy Policy Contact: [email protected]